
3 Non Negotiables for California Clinicians Doing EMDR via Telehealth

Yes. California licensed clinicians can deliver EMDR therapy over telehealth, provided the client is physically in a jurisdiction that permits it, informed consent is documented before the first session, and the platform meets HIPAA and California confidentiality standards. The three non-negotiables before you schedule a virtual session: confirm licensing and jurisdictional permissibility, secure documented informed consent, and lock in a compliant platform with an emergency plan attached to the client's actual location.
TL;DR:
Clinicians must verify the client's physical location at every session and confirm that the jurisdiction allows telehealth treatment before proceeding.
Informed consent for telehealth needs to be documented before the first session and repeated verbally at each session, including current address and treatment appropriateness.
Telehealth platforms require HIPAA and California confidentiality compliance, signed Business Associate Agreements, and secure data storage to meet legal standards.
Treating clients outside California is only permitted when the client’s current location allows it and the jurisdiction authorizes temporary telehealth practice.
Alvaradotherapy
Explore Trauma-Informed EMDR Support
Alvarado Therapy offers EMDR therapy and online care for Californians healing from trauma, anxiety, grief, and related challenges.
Table of Contents
What California Law Says About EMDR Telehealth Rules
The starting point for any California clinician doing telehealth is Business and Professions Code §2290.5. It defines telehealth as a mode of delivering health care, not a separate category of service with its own lighter standard. That distinction matters more than it sounds. If you wouldn't do something a certain way in person, you don't get to do it more casually just because the session happens over video.
BPC §2290.5 requires you to obtain and document consent, verbal or written, before delivering care via telehealth for the first time, consistent with California law. Skip that step and you're not just missing paperwork. The statute frames it as a professional conduct issue, meaning a documented consent failure can be treated the same way a licensing board treats other unprofessional conduct violations. Confidentiality and standard-of-care obligations carry over from in-person practice without modification. Telehealth doesn't lower the bar; it just changes the room.
Layered on top of the statute is a newer rule from the Board of Behavioral Sciences, which governs LCSWs, LMFTs, and LPCCs. The BBS Notice of Approval of Regulatory Action, codified at Title 16 §1815.5, becomes effective January 1, 2026, and it requires:
Informed consent consistent with BPC §2290.5, documented in the chart before initial telehealth delivery
Disclosure of the clinician's license number to the client
A documented list of local emergency resources near wherever the client is physically located
Verification of the client's location at the start of every session
That last point catches clinicians off guard. It's not a one-time check. If your client logs in from a different city, a hotel, or a relative's house, you're expected to note it and adjust your emergency resource list accordingly.
Psychologists fall under a separate but parallel framework from the Board of Psychology, which echoes the same core requirements: consent, competence with the technology, and standard-of-care parity with in-person work. The Medical Board of California frames telehealth the same way for psychiatrists delivering care through the same modality.
If you're relying on a blog post or a webinar recap instead of the actual regulatory text, you're one update behind. Regulator pages get revised; secondary summaries lag. Bookmark the primary sources, not someone's interpretation of them from two years ago.
Who Can You Legally Treat, and From Where?
Your California license lets you treat clients who are physically located in California, full stop. Where things get complicated is when either you or your client crosses a state line, even temporarily.
The Board of Psychology's telehealth guidance lays out the governing principle clearly: a California license authorizes telehealth to clients physically present in California. If a client travels out of state temporarily, and you want to continue sessions, you may only do so if the jurisdiction the client is currently in permits a California-licensed clinician to provide temporary telehealth care there. That permission is not automatic and it is not uniform. Some states have reciprocity provisions or temporary practice allowances; others don't, and treating a client there without checking first puts you outside your scope of licensure.
California is not a member of PSYPACT, the interstate compact that lets psychologists licensed in participating states practice across state lines under simplified rules; therefore, PSYPACT does not apply to California licensees. That means the compact shortcut other clinicians talk about in national forums simply doesn't apply here. If you're licensed only in California, PSYPACT gives you nothing.
A practical verification routine, run at the start of every session, keeps you covered:
Ask the client to state their current physical location, not just confirm a default address on file.
If that location is outside California, check whether that state or country allows a California-licensed clinician to provide temporary telehealth services there.
Document the legal basis for continuing the session, or pause care and refer to a locally licensed provider if the jurisdiction doesn't permit it.
Repeat the check every session, since travel status changes without warning.
The same logic runs in reverse if you, the clinician, are temporarily outside California. Your license follows you, but the client's protections and your authority to practice are tied to where they are sitting, not where you are. When in doubt, treat "client crossed a state line" as a pause-and-verify moment, not a footnote. For a deeper walkthrough of specific state-by-state scenarios, Alvarado Therapy's guide on practicing across state lines covers the situations that come up most often in practice.
What Must Informed Consent for Telehealth Include?
Consent for telehealth isn't a signature on a form you hand over once and forget. Both DHCS and the BBS treat it as an ongoing disclosure obligation with specific content requirements, and the details matter more than clinicians usually expect.
At minimum, your telehealth consent process, per the DHCS telehealth FAQ and BPC §2290.5, needs to cover:
The voluntary nature of telehealth, meaning the client can choose in-person care instead at any time
The client's right to request in-person treatment and how to do so
The specific risks and limitations of receiving therapy remotely, including technology failures and reduced ability to read nonverbal cues
A separate, distinct consent for audio-only sessions if that modality is used, since it carries different risk disclosures than video
How session data, recordings, and communications are stored and protected
Beyond the initial consent, the BBS's incoming rule adds per-session obligations that function almost like a pre-flight checklist. At the start of each session, you should state the client's current physical address out loud and log it, confirm the client's identity if there's any doubt, and note your own license number and type somewhere the client can reference it. You also need to make a clinical judgment, every time, about whether telehealth remains appropriate for that client's current presentation. A client escalating toward crisis may need an in-person referral even if they've done twenty stable telehealth sessions before.
Pro Tip: Build a one-line consent reconfirmation into your intake script rather than treating it as a separate form. Something like, "Before we start, can you confirm your current address and that you're comfortable continuing by video today?" takes ten seconds and creates a defensible verbal record if you note it in the session.
Store the signed initial consent form in a consistent chart location, and log verbal reconfirmations in your progress notes rather than a separate untracked file. For clients preparing for their first virtual session, Alvarado Therapy's guide to preparing for online therapy offers a useful client-facing version of these same disclosures.
How Do HIPAA and CMIA Apply to Virtual EMDR Sessions?
HIPAA sets the federal floor. California's Confidentiality of Medical Information Act (CMIA) adds state-specific expectations on top of it, and both apply in full to telehealth EMDR, not a scaled-down version of either.
On the technical side, your platform needs encryption in transit at minimum, and if any vendor stores or transmits protected health information on your behalf, you need a signed Business Associate Agreement with them before you send a single session through their system. Unique login credentials per clinician, rather than shared passwords, are table stakes. Secure, access-controlled storage for any session notes or recordings rounds out the baseline.
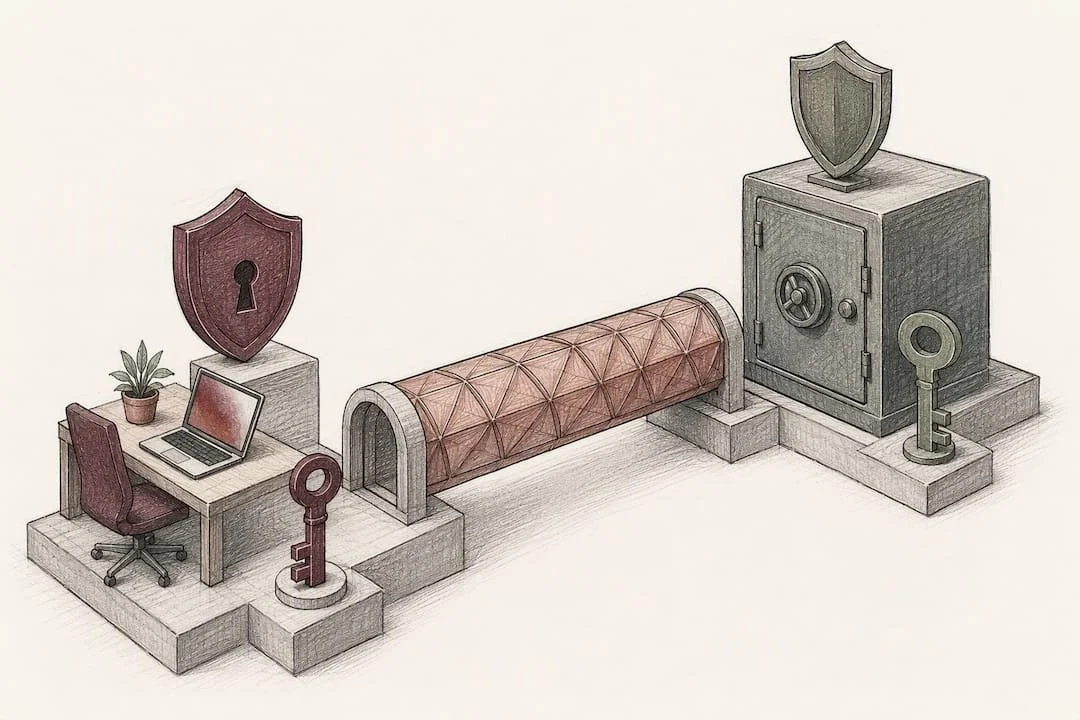
CMIA layers state-level notification duties on top of HIPAA's breach rules. If patient data is compromised, California law expects prompt notification to affected patients, and the standard for what counts as a reportable breach can be stricter than the federal baseline in certain scenarios. Treat CMIA as the stricter of the two standards when they diverge, not as a redundant footnote to HIPAA.
Before you commit to a telehealth platform for EMDR delivery, run it against this checklist:
Confirm the vendor offers a signed BAA, not just a privacy policy
Test video quality under realistic bandwidth conditions, since EMDR's bilateral stimulation components need visual clarity
Check screen-sharing limits if you use visual bilateral stimulation tools
Disable auto-recording by default and set an explicit, consent-backed recording policy
Verify the platform has patient-facing safety features, like an easy way to display a local number if the session drops
If you suspect a breach, the response sequence is the same regardless of platform: contain the exposure, document what happened and when you discovered it, notify affected patients per CMIA and HIPAA timelines, and keep a written record of every step you took. Clinicians assessing platform security more broadly sometimes bring in outside help; healthcare-focused IT tracking resources like CentriOps can support ongoing monitoring for practices managing multiple remote care tools.
Can EMDR's Eight-Phase Model Work Over Telehealth?
EMDR translates to telehealth reasonably well, but only if you refuse to cut corners on Phase 2. The American Psychological Association recognizes EMDR as an evidence-based treatment for PTSD, and that recognition assumes fidelity to the full eight-phase structure, not a trimmed remote version.
Phase 2, the preparation and stabilization phase, is where remote delivery tempts clinicians to move faster than they should. Clinical literature on remote EMDR delivery is direct about this: skipping or rushing stabilization work increases risk precisely because you have less ability to physically intervene if a client becomes dysregulated on camera. A client having a strong dissociative response in your office, you can respond to in the room. A client having that same response alone in their apartment needs stabilization skills already installed before you ever touch a traumatic memory network.
For remote bilateral stimulation, you have real options. Many clinicians use client-side tapping or self-administered eye movements guided verbally, while others use screen-based visual tracking tools built into telehealth-compatible EMDR platforms. Whichever method you choose, document the client's explicit agreement to that specific method in the chart. It's not interchangeable with in-person butterfly taps or a light bar, and clients should understand what they're consenting to try.
Practical safeguards worth building into every tele-EMDR case:
A documented, client-specific local emergency resource list, updated whenever the client's location changes
Clear behavioral red flags that trigger an immediate pause and pivot to grounding, rather than pushing through processing
A pre-agreed escalation pathway if the client becomes unsafe mid-session, including who to call and how
For EMDR intensives specifically, shorter and more frequent stabilization checks between processing blocks, since intensives compress a lot of activation into a short window
Pro Tip: For high-dissociation-risk clients, consider structuring the first one or two sessions purely around stabilization skill-building with no reprocessing at all, and revisit whether telehealth remains the right format before you move to Phase 3. If risk stays high, an in-person referral protects the client more than pushing forward remotely.
Alvarado Therapy's guide to preparing for EMDR therapy walks through what solid Phase 2 preparation looks like from the client's side, which is useful to share before a first remote session. For the evidence base itself, the research on EMDR treatment effectiveness is worth revisiting if you need to justify remote delivery to a skeptical supervisor or utilization reviewer.
How Do You Bill Medi-Cal for Telehealth EMDR Sessions?
Medi-Cal telehealth billing hinges on getting the modality and the modifier to match, and mismatches are one of the fastest ways to get a claim denied. DHCS's Medi-Cal telehealth policy covers synchronous video, audio-only, and asynchronous store-and-forward services, each with distinct rules.
The modifiers you'll use most:
Modifier 95 for synchronous, real-time video sessions, which covers most tele-EMDR
Modifier 93 for audio-only synchronous sessions, used when video isn't feasible or the client prefers it
Modifier GQ for asynchronous, store-and-forward services, which rarely applies to live psychotherapy but is relevant for some consult workflows
Audio-only sessions may have restrictions in some Medi-Cal contexts, particularly for establishing new treatment relationships. When video is available, it's safer to reserve audio-only for existing clients, and document client preference explicitly as separate consent.
Originating site and transmission fees use HCPCS codes Q3014 and T1014 with specific restrictions; audio-only sessions often have tighter limitations on these fees compared to video sessions.
Documentation must support billing, including modality used, client location, and sufficient clinical detail to justify the CPT code billed. Billing that does not reflect the actual session may be denied and could prompt audits.
What Should Your Telehealth EMDR Checklist Look Like?
A tight pre-session, during-session, and post-session routine keeps you compliant without turning every appointment into a paperwork exercise.
Before the session: Verify the client's expected location, confirm consent is signed and on file, test your platform's video and audio, and make sure you have that client's current local emergency contact information pulled up.
At the start of the session: Verbally confirm the client's name and current physical address, reconfirm consent to continue via telehealth today, state your license number if it's not already visible to the client, and briefly assess whether telehealth remains clinically appropriate given how they present.
After the session: Note any technical interruptions, document your safety assessment, flag any decision to refer to in-person care, and confirm the signed consent form is filed in its standard chart location.
Keep these elements in the same spot in every chart, whether that's a dedicated telehealth addendum or a standardized template field. An auditor, or a licensing board investigator, should be able to find your location verification and consent documentation in under a minute. If it takes longer than that, your system needs simplifying, not more forms.
How Alvarado Therapy Approaches Tele-EMDR in Practice
Running tele-EMDR responsibly comes down to sequencing. At Alvarado Therapy, Phase 2 preparation isn't rushed just because a session is virtual. Clinicians confirm the client's coping resources and grounding skills are solid before any reprocessing work begins remotely, and platform selection follows the same logic: video quality and screen-sharing reliability get tested before a client's first appointment, not discovered mid-session.
Jurisdictional checks and Medi-Cal documentation happen at intake and get revisited whenever a client's circumstances shift. Because Alvarado Therapy serves bilingual clients across Pasadena, Ventura, and telehealth statewide, crisis response planning accounts for language preference and local emergency resources specific to wherever the client is sitting that day.
— Juiced
Get Support Implementing Tele-EMDR the Right Way
Some therapy practices offer California clients a faster path to trauma care than piecing together a compliant setup on your own. Licensed clinicians can run EMDR sessions and EMDR intensives online with bilingual English and Spanish delivery and jurisdictional and consent protocols built into every intake.
If you're a client wondering what a first virtual EMDR session actually involves, the what to expect page walks through the process in plain terms, including how Alvarado Therapy handles PTSD and complex trauma cases specifically through its PTSD and complex trauma program. Clinicians who want to compare notes on tele-EMDR implementation, or who are considering a referral for a client whose case needs specialized trauma care, can book a consultation directly. Reach out this week if you have a client who needs trauma-focused care sooner rather than later.
This article is general information, not a substitute for advice from a qualified doctor. Consult a qualified healthcare professional about your own circumstances before acting on anything here.
Sources
FAQ
Does California allow out-of-state telehealth?
A California license only authorizes you to treat clients physically located in California. Providing temporary telehealth to a client who travels outside California is only permitted if that other state or jurisdiction allows a California-licensed clinician to practice there, and California does not participate in PSYPACT.
Can you do EMDR on telehealth?
Yes. EMDR can be delivered via telehealth as long as the eight-phase model stays intact, with particular care taken not to rush Phase 2 preparation and stabilization before reprocessing work begins.
What are the rules for telehealth in California?
Clinicians must document informed consent before the first telehealth session under BPC §2290.5, verify the client's physical location at every session under the BBS's incoming Title 16 §1815.5 standard, and maintain the same standard of care and confidentiality protections required for in-person treatment.
Can I do teletherapy across state lines?
Only if the client's current state permits a California-licensed clinician to provide temporary telehealth there; you're responsible for checking that jurisdiction's rules before continuing care, not assuming permission.
Does Medi-Cal cover EMDR delivered by telehealth?
Medi-Cal covers telehealth psychotherapy including EMDR when billed with the correct modality modifier, such as 95 for video or 93 for audio-only, and when documentation supports the CPT code billed.
